
Osgood-Schlatter & Sever’s Disease in Kids
Symptoms, causes, and treatment of the growth-plate pain behind knee and heel injuries in active kids
Growing Pains or Growth-Plate Injury?
If your active child has had knee pain this season and heel pain last year, it isn’t a coincidence. Osgood-Schlatter disease and Sever’s disease are both real, diagnosable growth-plate injuries — not just “growing pains” — and they share the same underlying cause.
Trusted Pediatric Foot & Ankle Care • Thousands of children treated by Dr. Mikkel Jarman, DPM, FACFAS
Why Two Different Growth Plates?
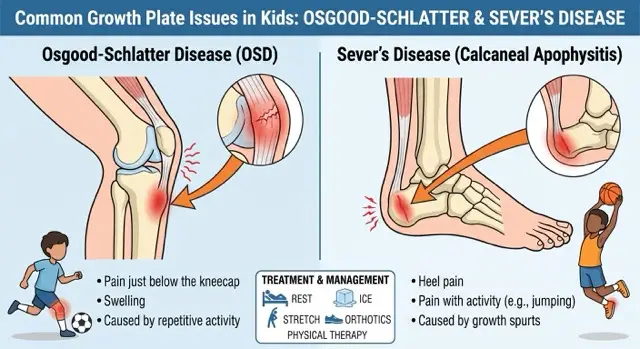
Osgood-Schlatter disease and Sever’s disease are both forms of traction apophysitis — overuse irritation where a tendon pulls on a growth plate that hasn’t finished hardening yet. They show up in different spots (the knee versus the heel), but the underlying mechanism, the age range, and the treatment approach are nearly identical.
That’s why active kids often develop one, the other, or both over the course of a growth spurt — and why the same conservative care resolves both.
Two Conditions, Same Root Cause
Osgood-Schlatter Disease
The Knee
Ages 10–15 (boys often 12–15, girls 8–12):
- Traction apophysitis at the tibial tuberosity, where the patellar tendon anchors onto the shin bone.
- Tender, sometimes visibly enlarged bump below the kneecap.
- Pain with running, jumping, kneeling, and stairs.
- Self-limited —resolves once the growth plate fuses
Sever's Disease
The Heel
Ages 8–14, most common cause of heel pain in this age group:
- Traction apophysitis at the calcaneus, where the Achilles tendon inserts into the heel bone.
- Heel pain that worsens with activity; positive “squeeze test” (gentle medial-lateral compression of the heel).
- Sometimes a limp.
- Also self-limited — resolves with skeletal maturity.
- Read our full guide to Sever’s disease and heel pain →
The Connection
Osgood-Schlatter and Sever’s disease are the same disease process happening at two different growth plates.
| Osgood-Schlatter (Knee) | Sever’s Disease (Heel) | |
|---|---|---|
| Pathophysiology | Both are apophysitis — an overuse traction injury at a tendon-to-growth-plate junction, not a fracture or a “real” tear. | |
| Trigger | Quad/patellar tendon tightens relative to bone growth. | Gastroc-soleus/Achilles tendon tightens relative to bone growth. |
| Risk Profile | Active kids in running and jumping sports — soccer, basketball, gymnastics, track. Growth velocity is the single biggest risk factor. | |
| Can Happen Together | A growth-spurt kid with tight lower-extremity muscles can develop apophysitis at multiple sites at once or in sequence — often grouped with Sinding-Larsen-Johansson (at the lower kneecap). | |
“Why does my kid have knee pain now and heel pain last year?” has a straightforward answer — growth. Neither condition means something is structurally wrong, and both respond well to the same conservative approach.
How We Treat It in Gilbert & Chandler
Management is shared across both conditions and rarely requires anything more than conservative care.
Activity Modification
Reducing — not eliminating — high-impact running and jumping while symptoms are active.
Ice & NSAIDs
Used as needed to manage pain and inflammation after activity.
Targeted Stretching
Quad and calf/Achilles stretching to reduce tension on the growth plate.
Supportive Footwear
Heel cushioning and, when needed, custom orthotics to reduce traction.
Patience
Both conditions resolve with skeletal maturity. Surgery is essentially never needed.
Frequently Asked Questions
Frequently Asked Questions
Can my child have Osgood-Schlatter and Sever's disease at the same time?
Yes. Because both conditions come from the same underlying process, an active child can develop apophysitis at more than one growth plate at once, or one after the other as growth continues. It's also common to see these grouped with Sinding-Larsen-Johansson syndrome at the kneecap.
Are these conditions serious or permanent?
No. Both are self-limited and resolve on their own once the growth plate fully closes. They're overuse traction injuries, not fractures or tears, and surgery is essentially never required.
Does my child need to stop playing sports?
Usually not entirely. Most kids do well with activity modification rather than full stoppage — reducing high-impact running and jumping while symptoms are active, then gradually returning as pain allows.
What is the squeeze test for Sever's disease?
Gentle medial-lateral pressure is applied to the heel. Pain with this compression, especially paired with activity-related heel pain in an 8- to 14-year-old, points strongly toward Sever's disease.
When should we see a pediatric foot and ankle specialist?
If your child has persistent knee or heel pain during a growth spurt, a visible bump below the kneecap, a limp, or pain that isn't improving with rest and stretching, it's worth having it evaluated at our Gilbert or Chandler office.